
Health communication
CONTENTS
Migraine
1. OVERVIEW
Migraine is a complex neurological disorder with a familial predisposition. It occurs episodically and is characterized by recurrent headache attacks accompanied by a variety of sensory symptoms. It is a multifactorial condition resulting from interactions between genetic and environmental factors, with headache being its most prominent manifestation.
The term “migraine” originates from the Greek word hemicrania, meaning “half of the head,” reflecting the common occurrence of unilateral headache. However, pain may also occur on both sides of the head, particularly in the frontal or occipital regions.
2. EPIDEMIOLOGY
Global prevalence
Migraine is one of the most common neurological disorders, affecting approximately 15–18% of the global population. Around 80% of people with migraine live in low- and middle-income countries, where access to specialized treatment remains limited.
Distribution by sex and age
Migraine is more common in women than in men, with a prevalence of approximately 18% in women and 6% in men. It most commonly affects people of working age, particularly those between 18 and 44 years.
Disease burden
Migraine is the second leading cause of disability worldwide when measured by years lived with disability and is the leading cause of disability among young women under the age of 50. The condition has a substantial impact on quality of life, education, and work performance.
3. PATHOPHYSIOLOGY
Migraine is a complex neurological disorder involving interactions among the nervous system, blood vessels, neurotransmitters, and genetic and environmental factors. The major mechanisms include:
Activation of the trigeminovascular system
This is a central mechanism in the development of migraine pain. When the trigeminal system is activated, sensory nerve fibers surrounding the dural blood vessels release neuroinflammatory mediators such as calcitonin gene-related peptide (CGRP). This leads to vasodilation, increased pain sensitivity, and headache.
Pain signals are subsequently transmitted through the brainstem and thalamus to the cerebral cortex, producing the characteristic sensation of migraine pain.
Role of neurochemical mediators
Several chemical mediators are involved in initiating and maintaining migraine attacks.
CGRP (Calcitonin Gene-Related Peptide): One of the most important mediators in migraine. It promotes vasodilation and increases the sensitivity of pain pathways.
PACAP (Pituitary Adenylate Cyclase-Activating Polypeptide), amylin, and nitric oxide (NO): These substances are involved in vascular regulation and activation of pain signaling pathways.
Serotonin: Plays an inhibitory role in the release of pain-related mediators and is also an important pharmacological target of several migraine treatments.
Ion channels, including TRP (Transient Receptor Potential), KATP (ATP-sensitive potassium channels), and BKCa (large-conductance calcium-activated potassium channels), contribute to the regulation of neuronal activity and vascular dilation.
Cortical spreading depression
Cortical spreading depression is associated with the aura phase in some patients. It consists of a wave of altered electrical activity that spreads across the cerebral cortex and produces temporary neurological symptoms such as flashing lights, blind spots, or sensory disturbances.
This process may also activate the trigeminal system and contribute to the subsequent headache phase.
Neural sensitization
In patients with migraine, the nervous system may become more sensitive than normal.
Peripheral sensitization: Pain fibers become more easily activated as a result of inflammatory mediators.
Central sensitization: Neurons in the upper cervical spinal cord, thalamus, and cerebral cortex become hyperresponsive, causing normally mild stimuli, such as touching the hair or exposure to light, to become painful.
Neural sensitization is an important mechanism contributing to the progression from episodic to chronic migraine.
Role of the hypothalamus and brainstem
The hypothalamus and brainstem are considered important regulatory centers in the migraine cycle. Changes in activity within these regions may occur one to three days before the onset of headache.
Disturbances in cerebral energy metabolism
The brains of people with migraine may experience impaired energy metabolism and increased oxidative stress due to mitochondrial dysfunction. This reduces the ability of neurons to adapt to changes and makes the brain more susceptible to activation and the initiation of migraine attacks.
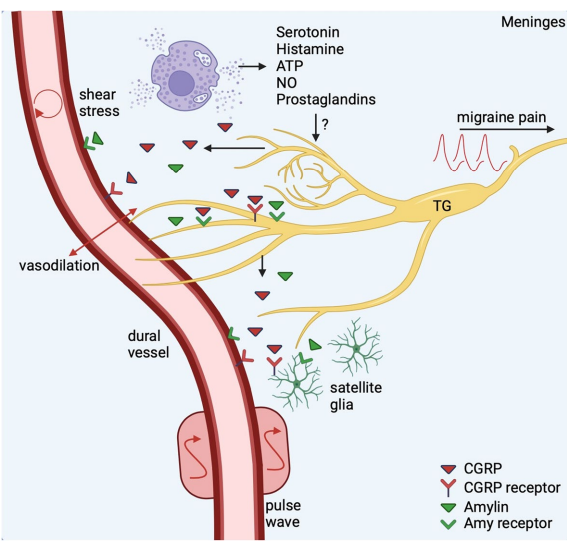
Figure 1. Role of CGRP and amylin in the trigeminovascular system
Raggi, Alberto, et al. “Hallmarks of primary headache: part 1-migraine.” The Journal of Headache and Pain 25.1 (2024): 189. https://doi.org/10.1186/s10194-024-01889-x
The figure illustrates the major components of the trigeminovascular system, including meningeal blood vessels, local mast cells, and trigeminal nerve fibers involved in migraine attacks. Binding of CGRP and amylin to their respective receptors causes vasodilation and generates shear stress within meningeal blood vessels.
CGRP also activates mast cells, promoting the release of various pain-related mediators such as serotonin, histamine, leukotrienes, prostaglandins, ATP, and nitric oxide. These mediators further stimulate nociceptive sensory fibers and increase CGRP release, thereby contributing to the persistence of migraine pain.
4. CLINICAL MANIFESTATIONS
A typical migraine attack lasts approximately 4–72 hours if untreated and may consist of four phases: prodrome, aura, headache, and postdrome.
Prodrome phase
The prodrome phase may occur several hours to two or three days before the onset of headache and may serve as an early warning that a migraine attack is developing.
Common manifestations include:
- Fatigue, mood changes, and irritability.
- Difficulty concentrating.
- Frequent yawning.
- Neck stiffness or discomfort.
- Increased thirst and frequent urination.
Aura phase
Approximately 20–30% of patients with migraine experience aura. Aura consists of temporary neurological symptoms that generally last 5–60 minutes and may occur before or during the headache phase.
Common forms include:
- Visual disturbances, which are the most common, such as flashing lights, zig-zag lines, bright spots, or temporary areas of visual loss.
- Sensory disturbances, including numbness or tingling sensations that often begin in the hand and spread toward the face or lips.
- Language disturbances, such as difficulty speaking, difficulty finding words, or temporary aphasia.
- Motor or brainstem symptoms, which are uncommon and may include weakness on one side of the body, loss of balance, or impaired coordination.
Headache phase
This is the most prominent phase and generally has the greatest impact on daily activities.
Typical characteristics of migraine headache include:
- Location: Usually unilateral, although pain may occur on both sides, particularly in the frontal or occipital regions.
- Quality: Pulsating or throbbing pain.
- Intensity: Moderate to severe, commonly rated at ≥5/10.
- Aggravating factors: Pain typically worsens with physical activity, walking, bending, or changes in posture.
Common associated symptoms include:
- Nausea or vomiting.
- Sensitivity to light and sound, often causing patients to seek a dark and quiet environment.
- Sensitivity to odors.
- Increased sensitivity of the scalp or face, causing pain even with light touch.
- Dizziness or impaired balance.
- Neck pain or stiffness.
Postdrome phase
After the headache resolves, patients may continue to experience symptoms for several hours or up to one day, including:
- Fatigue or exhaustion.
- Difficulty concentrating and reduced ability to work.
- A lingering dull headache or sensation of heaviness in the head.
- Persistent sensitivity to light and sound.
- Changes in appetite.
5. DIAGNOSTIC CRITERIA
According to the International Headache Society (IHS), the diagnosis of migraine is primarily based on the clinical characteristics of the headache and associated symptoms.
Migraine is divided into two major types: migraine without aura and migraine with aura.
Diagnostic criteria for migraine without aura
Migraine without aura is the most common form. Diagnosis is based on the following characteristics:
- At least five recurrent headache attacks with typical features.
- Each attack lasts 4–72 hours in adults if untreated or unsuccessfully treated.
The headache must have at least two of the following four characteristics:
- Location: Usually unilateral, although bilateral pain may occur.
- Quality: Pulsating, throbbing, or pounding pain.
- Intensity: Moderate to severe and sufficiently intense to interfere with daily activities.
- Relationship to physical activity: Pain is aggravated by routine physical activities such as walking, bending, or climbing stairs.
During the headache, at least one of the following groups of symptoms must also be present:
- Nausea and/or vomiting.
- Sensitivity to light and sound.
Diagnostic criteria for migraine with aura
Migraine with aura accounts for approximately 20–30% of cases and is characterized by temporary neurological symptoms that occur before or during the headache. These symptoms usually resolve completely.
The diagnostic criteria include:
- At least two migraine attacks accompanied by aura.
- The aura includes at least one of the following neurological symptoms:
a. Visual aura
Visual aura is the most common type, occurring in approximately 90% of patients with migraine with aura. Symptoms may include:
- Flashing lights.
- Zig-zag patterns or shimmering lights.
- Blind spots or temporary loss of vision.
b. Sensory aura
Symptoms may include:
- Numbness or tingling sensations.
- Symptoms commonly begin in the hand and then spread to the arm, face, or lips.
c. Language aura
Symptoms may include:
- Difficulty articulating words.
- Difficulty finding appropriate words.
- Temporary impairment of verbal expression.
Typical temporal characteristics of aura include:
- At least one symptom develops gradually over more than five minutes.
- Each symptom lasts approximately 5–60 minutes.
- Headache usually begins during the aura or within 60 minutes after the aura ends.
6. TREATMENT
Non-pharmacological treatment
Non-pharmacological approaches include:
- Getting sufficient sleep and maintaining consistent sleep and wake times.
- Maintaining adequate hydration.
- Eating regular meals and avoiding prolonged fasting or skipping meals.
- Limiting potential triggers such as excessive caffeine, monosodium glutamate, and artificial sweeteners.
- Practicing relaxation techniques, meditation, or yoga.
- Performing moderate-intensity aerobic exercise, for example 30–40 minutes several times per week.
Nutritional supplements for migraine prevention
Vitamin B2: Supports mitochondrial function and may help reduce the frequency of migraine attacks.
Magnesium: Helps stabilize neuronal activity and reduce excessive neuronal excitability.
Coenzyme Q10: Supports cellular energy metabolism.
Pharmacological treatment
Pharmacological management of migraine can be divided into two major categories: acute treatment and preventive treatment.
The choice of medication depends on headache severity, attack frequency, and individual patient characteristics.
Acute treatment
The goal of acute treatment is to provide rapid relief of symptoms and restore normal daily functioning. An important principle is to administer treatment as early as possible after headache onset to maximize effectiveness.
a. Non-specific acute medications
These agents are commonly used for mild to moderate migraine attacks.
Paracetamol: A basic analgesic that is commonly selected when a favorable safety profile is required, particularly in children, pregnant women, or patients who cannot take non-steroidal anti-inflammatory drugs (NSAIDs).
NSAIDs, including ibuprofen, naproxen, and diclofenac, are effective for the treatment of moderate migraine attacks. Naproxen has a relatively long duration of action and may therefore help reduce the risk of headache recurrence.
Antiemetics, such as metoclopramide and domperidone, may be used in patients experiencing nausea or vomiting. They may also improve the absorption of oral analgesic medications.
b. Migraine-specific acute medications
These medications are generally used for moderate to severe migraine attacks or when conventional analgesics are ineffective.
Triptans
Triptans are migraine-specific medications that act primarily as serotonin 5-HT1B/1D receptor agonists. Their effects include:
- Reducing intracranial vasodilation.
- Inhibiting the release of pain-related mediators such as CGRP.
Commonly used triptans include:
- Sumatriptan.
- Zolmitriptan.
- Rizatriptan.
- Eletriptan.
- Frovatriptan.
- Naratriptan.
Injectable sumatriptan has a rapid onset of action and may be particularly useful in patients with severe headache or significant vomiting.
Contraindications: Triptans should not be used in patients with ischemic cardiovascular disease, a history of myocardial infarction or stroke, peripheral vascular disease, or uncontrolled hypertension because of their vasoconstrictive effects.
Ditan: Lasmiditan
Lasmiditan selectively acts on 5-HT1F receptors and does not produce vasoconstriction, making it a potentially more suitable option for patients with cardiovascular risk.
Drowsiness is a common adverse effect; therefore, patients should avoid driving for at least eight hours after taking the medication.
Gepants for acute treatment
This group includes:
- Ubrogepant.
- Rimegepant.
- Zavegepant.
These drugs inhibit CGRP-related pain pathways. They do not cause vasoconstriction and are associated with a relatively low risk of medication-overuse headache.
Preventive Treatment
Preventive therapy is intended to reduce the frequency and severity of migraine attacks.
It is commonly considered in patients who:
- Experience four or more migraine attacks per month or have headaches on multiple days each month.
- Do not respond adequately to acute medication or experience significant adverse effects.
- Have specific migraine subtypes, such as chronic migraine, hemiplegic migraine, or migraine with brainstem aura.
a. Oral preventive medications
The general principle is to start treatment at a low dose and gradually increase the dose according to clinical response and tolerability.
Beta-blockers: Propranolol
Propranolol is effective for migraine prevention, particularly in patients with coexisting hypertension or anxiety.
Common adverse effects include fatigue and bradycardia.
Antiepileptic drugs
Topiramate
- Effective for both episodic and chronic migraine.
- May be beneficial for overweight patients because it can reduce appetite.
- Caution is required in patients with depression, kidney stones, or glaucoma.
Valproate
- Effective for migraine prevention but associated with several adverse effects, particularly the risk of fetal malformations.
- It should not be used during pregnancy or in women who may become pregnant.
Antidepressants
Amitriptyline and venlafaxine may be useful in patients with migraine accompanied by insomnia, anxiety, or tension-type headache.
Amitriptyline may cause drowsiness, dry mouth, constipation, and weight gain.
Other medications
Flunarizine: May be effective in patients with migraine associated with dizziness or vestibular migraine.
Candesartan: May be considered as an alternative in patients with hypertension who cannot tolerate beta-blockers.
REFERENCES
- Aguilar-Shea, Antonio L., Javier A. Membrilla, and Javier Diaz-de-Teran. “Migraine review for general practice.” Atención Primaria 54.2 (2022): 102208. https://doi.org/10.1016/j.aprim.2021.102208
- Raggi, Alberto, et al. “Hallmarks of primary headache: part 1-migraine.” The Journal of Headache and Pain 25.1 (2024): 189. https://doi.org/10.1186/s10194-024-01889-x
- Khan, Johra, et al. “Genetics, pathophysiology, diagnosis, treatment, management, and prevention of migraine.” Biomedicine & Pharmacotherapy 139 (2021): 111557. https://doi.org/10.1016/j.biopha.2021.111557
- International Classification of Headache Disorders (ICHD-3). https://ichd-3.org/2-tension-type-headache/
MSc. Kim Ngoc Son
MSc. Tran Khanh
